
When someone comes to my Houston practice asking for a mini facelift, I understand the appeal. They want their jawline back, they want to look like themselves, and they would rather have a smaller surgery with less recovery. I used to perform a procedure I called a mini facelift. I no longer offer that limited RT Mini Facelift approach, and the reason has a great deal to do with what I learned by seeing my patients years after their surgery.
The difference between a mini facelift and a deep plane facelift is not simply the size of the incision. It is what happens underneath the skin: how the deeper facial tissues are treated, whether the attachments holding those tissues in place are released, and which parts of the face and neck the surgery can realistically improve.
I want to explain the technique I used earlier in my career, why I moved away from it, and what I consider now when a patient asks for a modest, natural-looking change. This is my approach, not a claim that every surgeon’s mini facelift is the same or that every patient needs an extensive face and neck lift.
A smaller operation is not automatically the better operation. What matters is whether the operation is designed to correct the anatomy causing your concern.
START WITH THE TERMINOLOGY
What Does “Mini Facelift” Actually Mean?
There is no single standardized surgery that every surgeon performs under the name mini facelift. Some use it to describe shorter incisions. Others mean a smaller area of dissection, a limited SMAS procedure or an operation directed mainly at early jowling. Two patients can hear the same name and be offered substantially different surgeries.
That is why I do not think the name alone is useful. I want to know which tissues are being mobilized, which areas are being corrected, and whether the surgeon is treating the cheeks, jawline, neck or some combination of those regions.
What My Former RT Mini Facelift Involved
In the video below, I describe the limited facelift I performed roughly 10 to 20 years ago. I elevated a relatively small area of skin, worked with the superficial musculoaponeurotic system, or SMAS, through a limited dissection, tightened that supporting layer, and removed the redundant skin.
It was a legitimate surgical technique. Patients could see an improvement, the surgery was comparatively efficient, and the recovery could be easier than after a more extensive procedure. But the more important test for me was how those patients looked later.
WHY MY APPROACH CHANGED
What I Learned by Following My Mini Facelift Patients for Years
When you see a patient soon after surgery, you can evaluate healing, symmetry and the immediate change. That does not answer every question about how the result will age. As I saw some of my earlier mini facelift patients seven, eight and nine years later, I was not as satisfied with the longevity as I wanted to be.
I also found that the limited amount of tissue mobilization did not always give me the degree of natural repositioning I was trying to achieve. The operation could tighten the lower face, but I was not consistently freeing the deeper attachments that restricted where those tissues could move.
That experience made me reconsider the mechanics of the lift itself. Was I actually restoring the position of the descended tissue, or was I mostly pulling on tissue that remained tethered underneath? For the patients I was treating, that difference became increasingly important.
That is what I observed in my own patients, and it explains why I changed my approach. It does not mean that every limited SMAS facelift stops working at a particular year. Every facelift continues to age, and no technique permanently stops that process.
DR. ATHRÉ EXPLAINS
Mini Facelift vs. Deep Plane: Why I Changed My Technique
In this video, I use an anatomical model to explain the limited SMAS technique I once performed, what retaining ligaments do, and why I now usually favor deep plane repositioning when facelift surgery is appropriate.
UNDER THE SKIN
SMAS Tightening vs. Deep Tissue Repositioning
The SMAS is a network of fibrous and muscular tissue that helps connect facial expression muscles and surrounding soft tissues. It is an important layer in many established facelift techniques. The fact that one operation is described as a SMAS facelift and another as a deep plane facelift does not mean that one works on the SMAS and the other ignores it. What changes is how the tissues are approached and mobilized.
These illustrations show the structural difference between a more limited SMAS-tightening approach and a deep plane facelift that releases retaining ligaments and repositions deeper tissues.
This more limited approach tightens or plicates the SMAS rather than fully releasing retaining ligaments and repositioning the deeper facial tissues.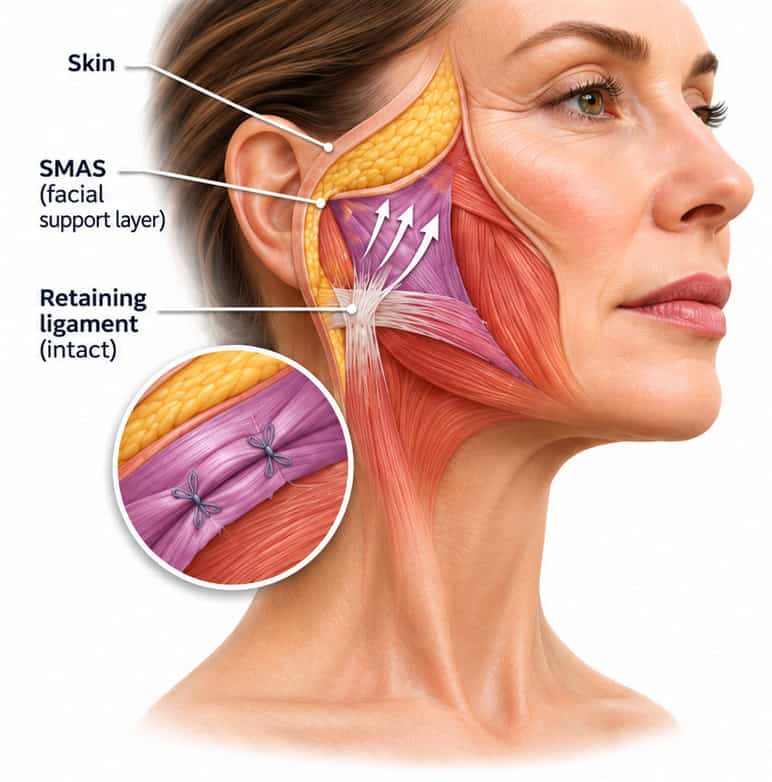
Limited SMAS Lift
By releasing key retaining ligaments, the deeper tissues can be mobilized and repositioned more naturally, with less dependence on skin tension.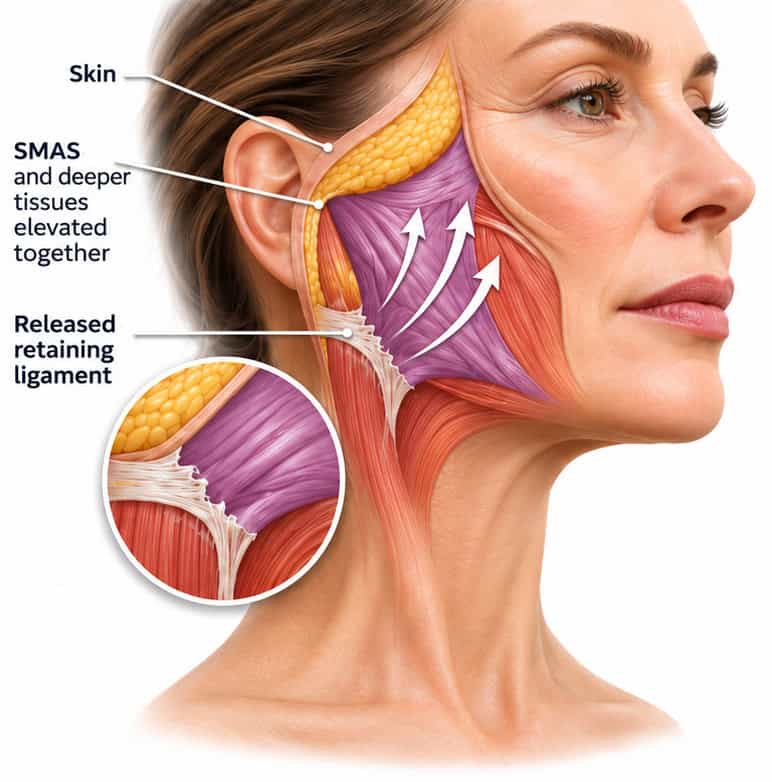
Deep Plane Facelift
How Limited SMAS Tightening Works
With a limited plication or imbrication approach, the surgeon can tighten or fold the SMAS to improve facial contour. This can be useful in properly selected patients. But if there is substantial cheek or jowl descent and important tethering attachments remain intact, there may be a limit to how far the tissue can be repositioned without adding unwanted tension.
What Changes in a Deep Plane Facelift
In a deep plane facelift, I work beneath the SMAS in selected regions and release the retaining ligaments necessary to mobilize the tissues I want to reposition. Rather than trying to produce the entire change by pulling the skin backward or tightening the SMAS in place, I can move the facial soft tissues more freely.
The zygomatic and mandibular retaining ligaments, along with other attachments through the cheek and lower face, help explain why the face does not behave like a loose sheet of skin. The anatomy matters because the point of fixation and the direction of movement affect what can be corrected.
I discuss these structures in greater depth in my article on facial retaining ligaments. For this comparison, the practical point is that tissue release gives me a different kind of mobility than simply adding more pull to a limited dissection.
My goal is not to pull the face harder. It is to free the correct attachments and reposition the tissue while keeping unnecessary tension off the skin.
COMPARING THE OPERATIONS
Mini Facelift vs. Deep Plane Facelift: The Differences That Matter
Extent of Surgery
A mini facelift usually describes a more limited intervention, but the exact incision and dissection vary among surgeons. A deep plane facelift is defined more by the plane of dissection and the release of appropriate attachments than by a predetermined incision length. Neither label tells you everything about how the neck will be treated.
What Gets Repositioned
My former mini lift relied more on limited SMAS mobilization and tightening. In my current deep plane approach, I aim to release the necessary retaining ligaments so the deeper facial tissues can be repositioned more completely. This is especially relevant when the concern involves descended cheeks, jowls or a transition between the lower face and neck that cannot be corrected with limited tightening alone.
Recovery
A smaller operation may involve less swelling or downtime, but it is not possible to promise a specific recovery based only on the words mini or deep plane. Recovery depends on the extent of dissection, whether neck work or other procedures are included, anesthesia, individual healing and postoperative care. I discuss the practical course of recovery in my post-operative healing resources.
Longevity
I changed my own technique in part because I wanted a more durable correction. But I cannot tell a patient that one facelift will last an exact number of years, or that every deep plane facelift will outlast every well-performed SMAS lift. The long-term result depends on the operation, the starting anatomy, healing and the natural changes that continue with age.
Safety
Every facelift carries risks, including bleeding or hematoma, infection, delayed wound healing, sensory changes, asymmetry, scarring and temporary or, rarely, persistent facial nerve weakness. Deeper dissection requires precise knowledge of facial nerve anatomy. I do not describe deep plane surgery as risk-free, just as I would not say that a smaller procedure has no meaningful risks.
CHOOSING THE RIGHT EXTENT
If I No Longer Perform the RT Mini Facelift, What Do I Offer Instead?
Patients often tell me they are not ready for a full facelift. Sometimes that is because they have only early changes. Sometimes it is because they assume a deep plane facelift must create a dramatic or unnatural result. Neither assumption tells me what operation, if any, is appropriate.
Early Cheek Descent With Little Neck Laxity
If the main concern is early midface descent, with little involvement of the neck, I may consider an endoscopic deep plane approach in an appropriate patient. This is a more focused way to address selected cheek changes, but it is not a substitute for a procedure that corrects significant jowling or neck laxity. I explain those differences separately in my article comparing mini facelifts with endoscopic deep plane lifting.
Jowling and Meaningful Neck Aging
If the jawline and neck have changed substantially, I am usually thinking about a deeper release and a coordinated face and neck plan. A limited cheek-focused procedure will not address prominent platysmal bands, significant loose neck skin or deeper neck fullness. This is where evaluation for a neck lift and a deeper lower-face correction becomes important.
Facial Descent Together With Volume and Skin Changes
Sometimes restoring tissue position is only part of the answer. Facial aging may also involve volume loss and changes in skin texture. My 4D Facelift™ approach allows me to plan structural lifting together with other appropriate components of facial rejuvenation, rather than expecting a facelift incision to solve every age-related change.
Minimal Aging or a Patient Who Is Not Ready
There are also people for whom I would not recommend facelift surgery yet. A small amount of perceived laxity, a concern that surgery cannot reliably correct or reluctance to accept surgical recovery may be reasons to defer. A consultation is not an obligation to have an operation.
Does a Deep Plane Facelift Have to Look More Dramatic?
No. The depth of a surgical plane is not a measure of how different a patient must look. I can use a more complete release of the supporting tissues while still making conservative decisions about how far they move and what the final contour should be.
Patients sometimes equate “less invasive” with “more natural.” But a smaller surgical field does not automatically produce a subtler-looking result, and a deeper operation does not require an aggressive appearance. Facial proportions, tissue position, vectors of lift and skin closure all matter.
What I do not want is to recommend a limited operation because the name sounds less intimidating, then discover that it could not adequately address the patient’s main concern. The more useful conversation is about the amount and location of aging, the result the patient wants and the recovery or risk they are prepared to accept.
PREPARING FOR CONSULTATION
What Should You Ask Before Choosing a Facelift Technique?
I would ask a surgeon to explain the operation in anatomical terms, not just by its name. Where will the incisions be? What part of the SMAS is being treated? Are the retaining ligaments being released, and where? What happens to the neck? Is additional fat transfer or another procedure needed to accomplish the stated goal?
It is also reasonable to ask to see actual before and after photographs of patients with anatomy similar to yours, including follow-up beyond the immediate postoperative period when available. Ask about the surgeon’s experience with the proposed technique, the specific risks in your case and what the operation is unlikely to improve.
If you want a broader explanation of terms such as SMAS, deep plane and 4D, I cover them in Facelift Techniques Explained. This article has a more specific purpose: to explain why my own approach moved away from limited mini lifting and how that affects the recommendations I make today.
RESULTS IN CONTEXT
What My Current Facelift Planning Looks Like in Actual Patients
These are examples from my facelift gallery, showing different patients and different combinations of facial rejuvenation. They are not a head-to-head clinical comparison between mini and deep plane facelifts, and the photographs should not be used to attribute an entire result to one surgical step.
The point is that I plan around the patient’s anatomy and concerns rather than treating everyone with the same limited operation. Some of the cases shown also involved neck surgery, eyelid surgery, fat transfer or other procedures.
BEFORE & AFTER
Facelift Patient Results


Why I Choose the Facelift Based on Anatomy, Not the Label
Performing limited mini facelifts earlier in my career taught me something valuable. A quick improvement and an easier early recovery are not the only things I want from surgery. I want to understand how the result is likely to behave as the patient continues to age, and I want to correct the underlying position of tissues rather than depend on tightening alone when that would not be enough.
Today, I generally use some form of deep plane repositioning when a facelift is appropriate, with the extent of the operation determined by the anatomy. That does not mean every patient needs the same surgery, and it certainly does not mean every patient needs surgery right now.
I no longer offer the RT Mini Facelift because it stopped matching what I wanted to accomplish for my patients. The better question is not how small I can make the operation, but how precisely I can match the operation to the problem.
FREQUENTLY ASKED
Mini Facelift vs. Deep Plane Facelift FAQs
These questions clarify the surgical terminology, Dr. Athré’s current approach and what research can and cannot tell us about results.
Does Dr. Athré still perform the RT Mini Facelift?
No. I previously performed a limited SMAS-based operation called the RT Mini Facelift, but I no longer offer that technique. After examining my own long-term results, I changed my approach to favor deeper tissue mobilization when facelift surgery is appropriate. This is a decision about my practice, not a claim that all SMAS techniques are ineffective. A 2025 systematic review comparing SMAS and deep plane techniques found meaningful outcomes with both approaches and limited evidence of universal superiority.
Is a mini facelift a real operation?
Yes. Surgeons perform real operations described as mini facelifts, but the label does not refer to one standardized anatomical technique. It may involve shorter incisions, limited dissection or SMAS tightening. The foundational description of the SMAS explains the anatomy underlying many established facelift techniques; the term “mini” alone does not tell you how that layer will be treated.
What is the biggest anatomical difference between a mini and deep plane facelift?
In the limited technique I once performed, I primarily tightened the supporting tissues with relatively little deep mobilization. In a deep plane approach, I release selected retaining ligaments to mobilize and reposition the facial tissues more freely. The original description of the cheek’s retaining ligaments and a study of the superficial and deep facial fascia explain the anatomical attachments involved.
Does a deep plane facelift always look more natural?
No technique guarantees a natural result. Deep plane dissection allows a surgeon to reposition tissues after selected attachments have been released, which can help reduce reliance on skin tension. But the final appearance also depends on surgical planning, vectors, proportions, skin redraping and judgment. A 2025 systematic review of deep plane and SMAS facelifts reported high satisfaction with both methods, not an absolute guarantee for either.
Does a deep plane facelift last longer than a mini facelift?
In my own practice, concerns about the durability of my earlier limited lift helped motivate my change in technique. However, published research does not establish a universal lifespan for either operation. The systematic review on long-term satisfaction concluded that both deep plane and SMAS techniques can produce robust outcomes, while noting ongoing debate over comparative durability.
Is recovery always faster after a mini facelift?
Not always. A limited procedure may involve less surgical work, but recovery depends on what was actually performed and on individual healing. It is not possible to assign a reliable downtime from a marketing name alone. A comparative systematic review found that differences among studies and surgical techniques make broad conclusions difficult. I discuss realistic recovery in relation to the planned operation, not simply its label.
Is deep plane surgery riskier because it goes deeper?
Deep dissection involves important facial nerve anatomy and requires appropriate training and precision. Both deep plane and SMAS facelift procedures carry risks. A 2025 meta-analysis of facelift safety found broadly comparable safety profiles, while emphasizing that the available comparisons do not justify declaring one technique universally safer.
What if I have only early sagging and do not want a full facelift?
Then I evaluate whether surgery is worthwhile at all and exactly where the change is occurring. A selected patient with early midface descent and little neck laxity may be considered for a focused endoscopic approach, whereas more significant jawline and neck changes need a different plan. Anatomy is more useful than age alone. The review of SMAS and deep plane facelift techniques also supports individualized technique selection rather than a single operation for everyone.


