
If you start researching facelift surgery, it does not take long before the names become confusing. SMAS facelift. Deep plane facelift. Extended deep plane. Mini facelift. Vertical Restore®. 4D Facelift™. Some of these names describe meaningful differences in surgical technique. Others describe a particular surgeon’s approach to facial rejuvenation.
I think there is a better way to understand the choices. Instead of starting with the name of the facelift, start with the anatomy.
What layer is being treated? Which tissues are actually being repositioned? Are the retaining ligaments being released? How much of the face and neck needs to be addressed? And what else besides sagging has changed?
The name of the facelift matters less to me than understanding what the surgery is actually doing underneath the skin.
What Is a SMAS Facelift?
The SMAS, or superficial musculoaponeurotic system, is a layer of fibrous and muscular tissue beneath the skin. Modern facelift surgery often works with this layer rather than asking the skin alone to carry the correction.
There are different ways to treat the SMAS. It can be tightened, folded, repositioned or dissected to varying degrees depending on the technique and the surgeon.
A well-performed SMAS facelift can produce an excellent result. I do not think it is useful to describe every SMAS technique as outdated or every deep plane technique as automatically better.
The important question is how much mobility I need to create in the tissues to correct the particular pattern of aging in front of me.
What Is a Deep Plane Facelift?
A deep plane facelift changes the dissection so I can work beneath the SMAS in specific areas and release the retaining ligaments that tether the facial tissues to deeper structures.
That release is the part I want patients to understand.
If I am trying to reposition tissue while it is still firmly tethered, there is a limit to how freely that tissue can move. By releasing the appropriate retaining ligaments, I can mobilize the deeper facial tissues and reposition them as a unit rather than relying primarily on pulling the skin.
INSIGHTS FROM DR. ATHRÉ
Watch What a Deep Plane Facelift Actually Does
I use Henrietta, my silicone facial model, to show what happens when I pull the SMAS while the deeper attachments remain intact, and what changes when I release the retaining ligament that is restricting movement.
Why the Retaining Ligaments Matter
The face is not a loose stack of tissues. It has structural attachments that help hold the soft tissues in position. These facial retaining ligaments are part of the architecture I have to understand when planning a facelift.
You can see the principle in the Henrietta demonstration. Pulling on the tissue while it remains tethered produces one kind of movement. Releasing the appropriate tether changes how that tissue can be mobilized.
That does not mean every ligament should be released in every patient. It means the surgical plan has to account for where the tissues are fixed and where I need mobility to restore the contours I am trying to improve.
I am not trying to overpower the anatomy with tension. I am trying to understand the anatomy well enough to move the right tissues in the right direction.
SMAS Facelift vs. Deep Plane Facelift
The difference is easier to understand visually. Both techniques work below the skin, but they create mobility differently.
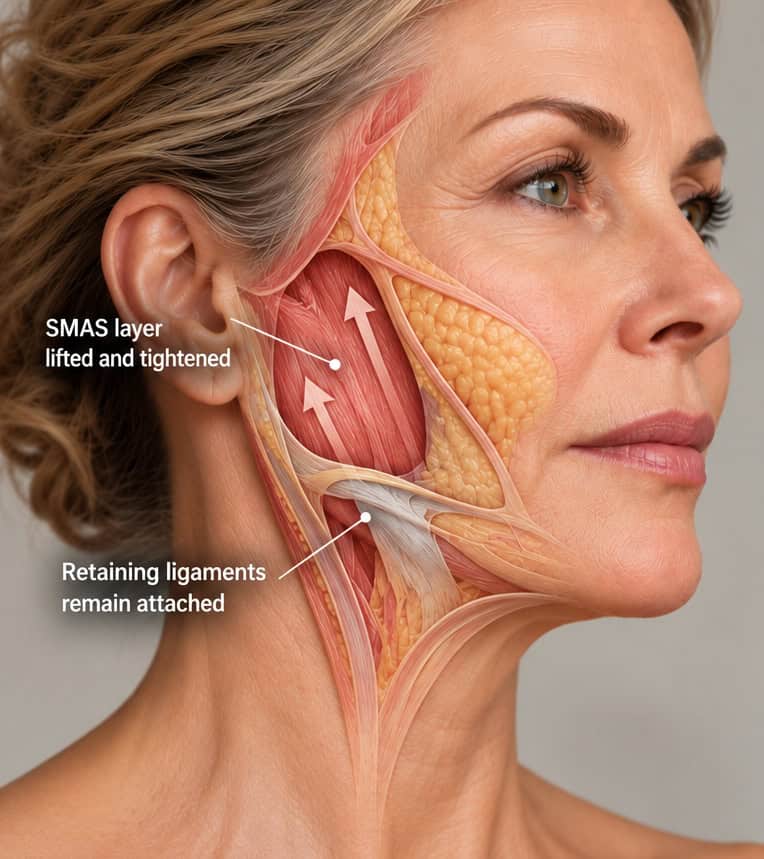
SMAS Facelift
The SMAS provides structural support beneath the skin and can be tightened or repositioned using several different techniques.
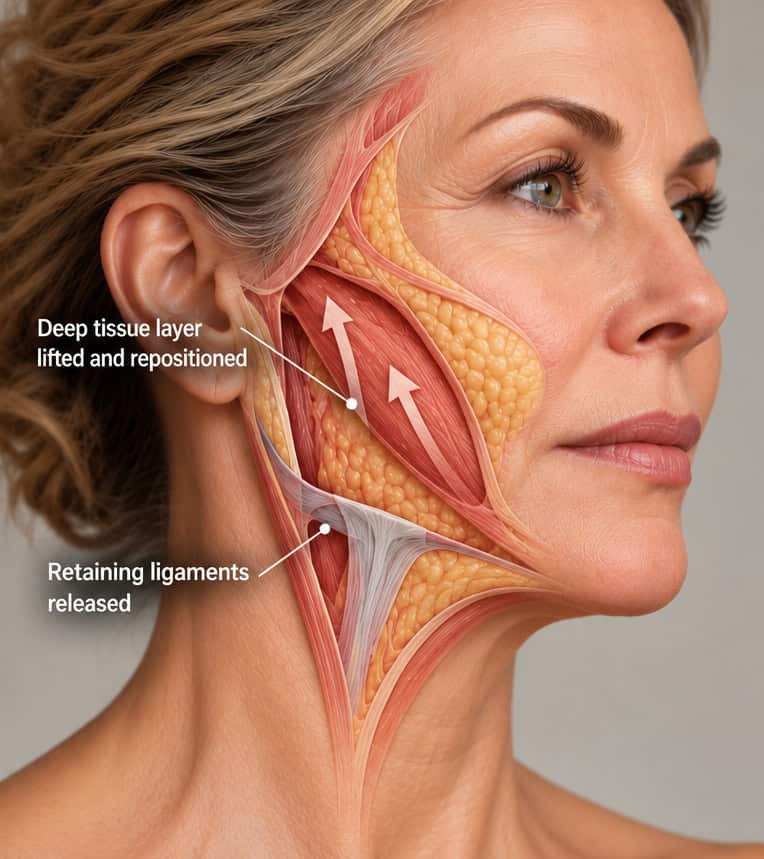
Deep Plane Facelift
Releasing selected retaining ligaments allows deeper facial tissues to be mobilized and repositioned with less dependence on skin tension.
I use a deep plane approach when I believe that deeper release and mobilization will help me restore the relationships I am trying to improve, particularly through the cheek, lower face and jawline.
That does not make every patient a deep plane patient. Technique should follow anatomy, not the other way around.
Why I Do Not Want the Skin Carrying the Facelift
Skin is important, but I think of it as the covering rather than the primary structural support of the facelift.
If I depend heavily on skin tension to create the result, I am asking the skin to do a job that deeper tissues are better suited to perform.
My preference is to create the structural change underneath, remove only the appropriate amount of excess skin and then redrape the skin over the repositioned tissues without asking it to create the lift by itself.
I want the deeper tissues to establish the new contour. I want the skin to lie naturally over that contour.
What Is an Extended Deep Plane Facelift?
“Extended deep plane” generally describes taking the deep plane dissection and release farther so that a broader area of the face can be mobilized.
The deep plane facelift I perform is technically an extended deep plane approach. I release the retaining structures necessary to mobilize the tissues I am treating and combine that facial work with a deep neck lift when the neck anatomy requires it.
But I do not think the word “extended” should become another marketing contest. More dissection is not automatically better surgery. I want enough release to accomplish the correction while respecting the anatomy around it.
What About a Mini Facelift?
“Mini facelift” is one of the least specific terms in facial plastic surgery. It can mean very different things depending on who is using it.
In some practices, mini describes a limited skin or SMAS procedure. My RT Mini Facelift is a more limited deep plane approach intended for selected patients with earlier or less extensive facial aging.
I do not choose it simply because someone is younger or wants less downtime. I choose it when the anatomy does not require the extent of surgery I would use for a full facelift.
What Is a Vertical Restore® Facelift?
Vertical Restore® is a branded facial rejuvenation approach developed by Dr. Amir Karam. It uses a deep plane foundation and emphasizes a more vertical direction of tissue repositioning rather than simply pulling the face backward toward the ears.
I agree with the principle that vector matters. I have used a strong vertical component in my facelift surgery for many years because facial aging is not simply a sideways problem.
Where my approach differs is not that I believe there is one uniquely correct direction of pull. I am looking at where the tissues started, where they have moved and what vector restores that patient’s anatomy most naturally.
Different surgeons can use related anatomical principles and still develop different ways of applying them.
How Is My 4D Facelift™ Different?
A facelift primarily addresses tissue position. Facial aging is broader than tissue position alone.
As the face ages, tissues descend, but facial volume can also change and the skin itself changes in texture and quality. Correcting only one of those problems can leave the rejuvenation incomplete.
That is the thinking behind my 4D Facelift™. The deep plane facelift provides the structural lifting foundation. I can then use facial fat transfer where volume restoration is appropriate and address skin quality when it is part of what is making the face look older.
I do not add those things because every patient needs the same package. I add them when they address a separate component of aging that the lift itself will not fully correct.
A facelift can reposition the face beautifully and still leave other dimensions of aging untreated. I want to correct what has actually changed, not simply perform a bigger lift.
INSIGHTS FROM DR. ATHRÉ
Why the Layer Being Lifted Matters
I walk through the skin, SMAS and deep plane, then return to Henrietta to demonstrate how ligament release changes tissue mobility. I also show a patient more than three years after facelift surgery because I think long-term results are more useful than judging a technique from an early postoperative photograph.
What Makes a Facelift Age Well?
I want a facelift to look good when the early tightness and swelling are gone. More importantly, I want the patient to continue looking like herself as the result matures.
That is why I pay attention to the layer being treated, the amount of tissue release, the direction of repositioning, skin tension, incision placement, volume and the relationship between the face and neck.
No facelift stops aging. The tissues continue to change after surgery. I am trying to create a durable structural correction that ages with the patient rather than a temporarily tight face.
When you look at my facelift before and after results, I would encourage you to look beyond how sharp the jawline is. Look at whether the patient still looks recognizable. Look at the cheeks, mouth, ears, hairline and neck. Look at the face as a whole.
How I Choose the Right Facelift Technique
I do not start a consultation by deciding which trademark or procedure name I want to use.
I look at the midface. I look at the jowls and jawline. I look underneath the chin and through the neck. I look at facial volume, skin quality, skeletal support and previous surgery. Then I listen to what the patient actually wants to change.
A patient with relatively early lower-face aging may not need the same surgery as someone with substantial midface descent, jowling and neck laxity. A patient with significant volume loss may need something different from a patient whose primary problem is tissue position.
This is also why my training matters to the way I think about these procedures. I trained in head and neck surgery before specializing in facial plastic surgery, and I tend to approach facial rejuvenation by asking how the anatomy works before deciding how I want to change it. You can read more about my training and philosophy on my Dr. Raghu Athré page.
I do not want to fit your face into my facelift. I want to choose the surgery that fits your face.
BEFORE & AFTER
Facelift Results


FREQUENTLY ASKED
Questions About Facelift Techniques
These are some of the questions patients ask when comparing SMAS, deep plane and other facelift approaches.
Is a deep plane facelift better than a SMAS facelift?
Not for every patient. Both approaches can produce excellent results. A 2025 systematic review and meta-analysis of SMAS and deep plane facelifts found high satisfaction with both techniques. I choose based on the anatomy I need to mobilize rather than assuming one technique is universally best.
Does a deep plane facelift last longer than a SMAS facelift?
We do not have strong comparative evidence proving that it always does. A 2025 systematic review of deep-layer facelift techniques found that deep plane approaches have not yet been shown to provide greater longevity than well-performed SMAS techniques. Surgical technique, anatomy and aging all affect durability.
Is a deep plane facelift more dangerous because it is close to the facial nerve?
Deep plane surgery requires detailed knowledge of facial nerve anatomy because the dissection occurs near nerve branches. However, a large systematic review comparing SMAS and deep facelift techniques found similar nerve-injury rates overall, with most reported injuries being temporary.
Why are retaining ligaments important in a deep plane facelift?
Retaining ligaments tether facial soft tissue to deeper structures. Releasing selected ligaments creates mobility so the deeper tissues can be repositioned. Detailed deep plane anatomical research describes these ligaments, facial nerve relationships and the sub-SMAS spaces used during surgery.
Does deep plane surgery improve the midface more than SMAS surgery?
It may in some patients, but the evidence is not definitive. A recent systematic review of more than 10,000 facelift patients found some evidence favoring deep techniques for midface rejuvenation, while noting that direct comparative studies remain limited.
How long can a deep plane facelift last?
There is no expiration date. In one 30-year surgical series, patients who returned for another facelift did so an average of 10.9 years after their primary deep plane facelift. That study included only patients who eventually had revision surgery, so it should not be interpreted as a guaranteed lifespan for every result.
Is a mini facelift the same thing as a SMAS facelift?
No. “Mini facelift” describes the extent of a procedure inconsistently and does not identify one anatomical technique. A mini procedure may involve skin, SMAS or a more limited deep plane approach. I recommend asking exactly which tissues are being treated rather than relying on the word “mini.”
Do deep plane facelifts have fewer complications?
Current evidence does not establish that. Comparative research has found broadly similar safety profiles, although reported rates vary between studies. A systematic review comparing modern SMAS and deep techniques concluded that limited comparative data prevent definitive claims that one is safer overall.
How should I choose between facelift techniques?
Start with the surgeon and your anatomy rather than the procedure name. Current evidence supports individualized technique selection because both SMAS and deep plane approaches can work well. The right choice depends on which tissues need to move, the extent of aging, your previous surgery and the result you are trying to achieve.



