
If you’re considering a mini facelift, you’re probably not asking me to completely rejuvenate an aging face and neck. You’re usually seeing something earlier: a little softness along the jawline, some change through the cheek, or a face that simply doesn’t look as sharp as it did a few years ago.
I perform two different procedures for patients in this stage of facial aging: my RT Mini Facelift and an endoscopic vertical-vector deep plane midface lift.
They are not two versions of the same surgery, and I don’t consider one universally better than the other. They approach the face differently, they correct different anatomy, and the right choice depends on where your face has actually changed.
That’s the distinction I want to explain in this article, because the procedure name matters much less to me than choosing the surgery that actually matches the problem I’m trying to correct.
The question isn’t which surgery is better. The question is which surgery is designed to correct the anatomy I see when I examine your face.
THE LOWER FACE AND NECK
What I Mean by an RT Mini Facelift
The term “mini facelift” can be confusing because it does not describe one standardized surgery. Different surgeons can use the same name for very different operations.
My own approach has also changed over time. When I talk about an RT Mini Facelift today, I am not talking about simply making a shorter incision, tightening the SMAS and trimming some skin.
The patient I am generally considering for an RT Mini has aging concentrated primarily along the jawline and neck, with relatively little descent through the midface. These patients are often relatively slender and may still have a good cheek position, but they are beginning to lose the clean transition from the face into the neck.
During surgery, I am working with the deeper retaining structures that are contributing to that pattern. Depending on the patient’s anatomy, that can include release of the masseteric ligament, mandibulocutaneous ligament and the platysma attachment near the sternocleidomastoid muscle. I may also release part of the zygomatic ligament when the anatomy requires it.
INSIGHTS FROM DR. ATHRÉ
Will an RT Mini Facelift Actually Work for You?
I explain the anatomy I look for when deciding whether an RT Mini Facelift is actually the right surgery for a patient.
THE MIDFACE
What Is an Endoscopic Vertical-Vector Deep Plane Midface Lift?
The endoscopic procedure approaches facial aging from a different direction.
Instead of making an incision in front of the ear, I work through incisions hidden in the hair-bearing scalp. An endoscope gives me visualization as I enter the deep plane, release the appropriate retaining ligaments and reposition the descended tissues.
This is still deep plane surgery. The difference is the access and the direction in which I can reposition the tissues.
Because the access is from the scalp, this procedure lends itself to a more vertical vector. That makes it particularly useful when the problem I am trying to correct is descent through the cheek and midface.
It is sometimes described as a “scarless” facelift, but I don’t think that is an accurate description. There are incisions. They are simply placed within the hair rather than in front of the ear.
There is another very important limitation: I am not removing loose facial or neck skin with this approach and it does not directly correct significant neck aging.
That means skin quality matters. A patient with good elasticity, midface descent and a jawline and neck they are genuinely happy with can be a very different candidate from someone who has significant loose skin, jowling or neck laxity.
INSIGHTS FROM DR. ATHRÉ
Who Is an Endoscopic Facelift Right For?
I explain how an endoscopic facelift works, where the incisions are placed, what the procedure can correct and which patients are best suited to this approach.
TWO DIFFERENT PROBLEMS
These Procedures Do Not Treat the Same Anatomy
This is the most important part of the comparison. If you come into my office asking whether the RT Mini or the endoscopic lift is better, I can’t answer that until I examine your face.
If I see a cheek that is still in a good position but early jowling, loss of jawline definition and early neck laxity, I’m thinking about the lower face and neck. That’s the pattern that can push me toward an RT Mini Facelift.
If I see good skin elasticity, a relatively good jawline and neck, but descent through the cheek and midface, that’s a different problem. That anatomy can push me toward an endoscopic vertical-vector deep plane midface lift.
Focused primarily on early aging through the lower face, jawline and neck when there is relatively little midface descent.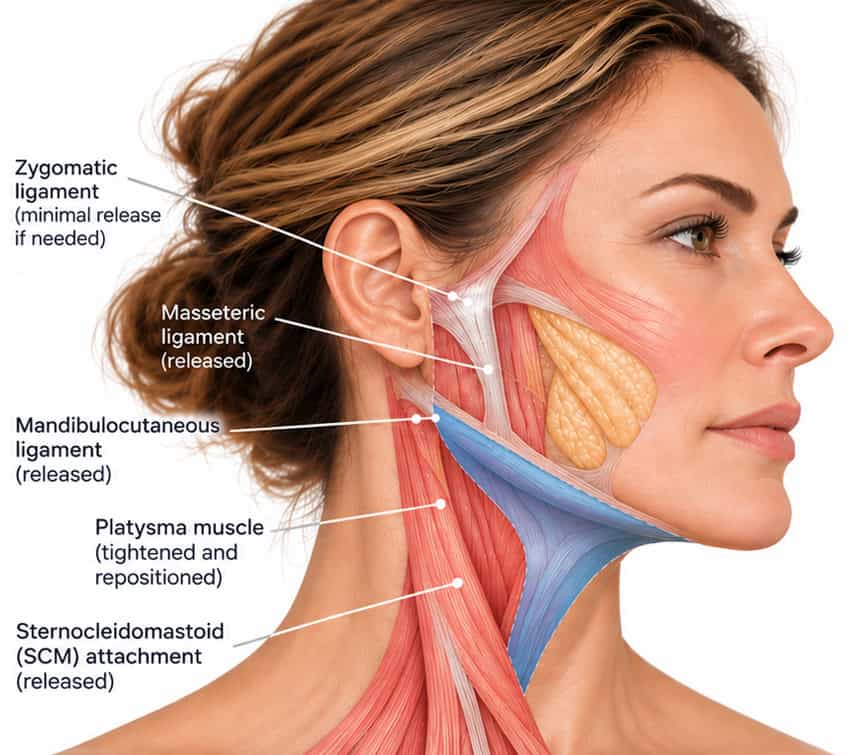
RT Mini Facelift
Focused primarily on the cheek and midface in a patient with good skin elasticity and little need for neck correction.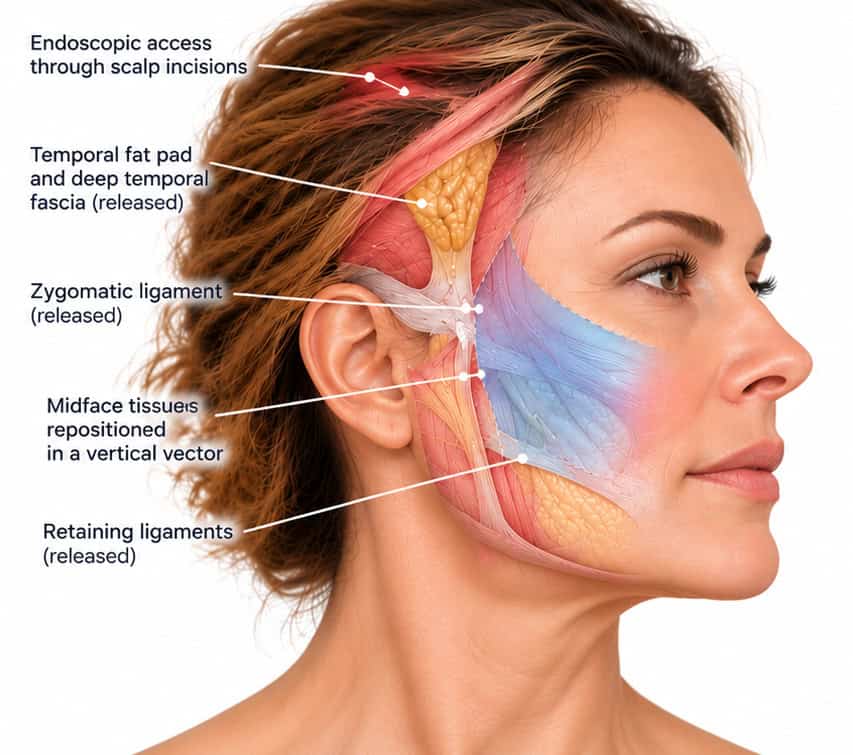
Endoscopic Vertical-Vector Deep Plane Midface Lift
One procedure is primarily solving a lower-face, jawline and neck problem.
The other is primarily solving a midface and cheek-position problem.
How I Decide Which One Makes Sense
This is where procedure names become much less important to me. I am looking at your anatomy.
Where is the aging occurring?
The first thing I want to know is where the face has actually changed.
If the dominant problem is the jawline, lower face and upper neck while the cheek remains relatively well positioned, an RT Mini may make sense.
If the dominant change is descent of the cheek and midface while the jawline and neck remain relatively good, the endoscopic approach becomes much more interesting.
How much loose skin is present?
This matters because the endoscopic procedure does not remove facial or neck skin.
A patient with good elasticity can often accommodate vertical repositioning of the deeper tissues very differently from someone who already has substantial skin laxity.
What does your neck look like?
This is one of the clearest distinctions between these procedures.
If your neck is part of what bothers you, I need a procedure that actually gives me the ability to address it. An endoscopic midface lift is not a substitute for neck correction.
What result are you actually trying to achieve?
Sometimes a patient comes in asking for a specific procedure because she likes the incision, the recovery or something she saw online. I understand that, but those factors cannot override the anatomy.
The procedure has to be capable of correcting the thing that bothers you.
I am not trying to fit your face into a procedure. I am choosing the procedure that fits your face.
DIRECTION MATTERS
Why the Direction of the Lift Matters
Facial aging does not happen in exactly the same way in every patient and I don’t want to reposition every face in exactly the same direction.
The scalp access used during an endoscopic lift allows me to approach descended midface tissues from above. That makes a more vertical repositioning of the cheek possible.
The RT Mini is addressing a different territory. When the problem is concentrated along the lower face, jawline and neck, I need access that lets me work with the structures responsible for those changes.
The direction and extent of the surgery should follow the direction and extent of the aging.
What About Recovery?
Neither of these is a nonsurgical treatment. They are both real surgeries performed in deeper facial planes, so I don’t want patients choosing between them simply because one sounds smaller.
The recovery is also somewhat different because I am working in different areas.
With the endoscopic approach, swelling can be concentrated through the cheek and temporal region because that is where I am working. For the right patient, I generally describe about seven to eight days of meaningful downtime, although swelling continues to improve after that.
With an RT Mini, the recovery reflects the work being performed through the lower face, jawline and neck.
I would rather have you accept the appropriate recovery for the right surgery than choose the wrong surgery because the name sounds easier.
WHEN MORE IS NEEDED
Sometimes Neither Procedure Is Enough
There is another possibility that has to be part of this discussion: sometimes neither limited approach is the right answer.
If I see more significant jowling, substantial loose skin, platysmal banding or aging that involves several regions of the face and neck, trying to force that anatomy into a smaller procedure can compromise the result.
That is when I may recommend a more comprehensive facelift and neck lift instead.
This is why I don’t like choosing surgery based on age or based on the procedure name a patient walked in requesting. Two people of the same age can have completely different anatomy and need completely different operations.
So, RT Mini or Endoscopic Deep Plane?
If your aging is concentrated primarily along the jawline, lower face and neck with relatively little midface descent, I may consider an RT Mini Facelift.
If your primary issue is descent through the cheek and midface, your skin still has good elasticity and you are genuinely happy with your jawline and neck, an endoscopic vertical-vector deep plane midface lift may make more sense.
If aging has progressed across the midface, jawline and neck with more significant skin laxity, neither may be enough and a more comprehensive approach may be appropriate.
I perform both of these procedures. They solve different problems. The right surgery is the one designed to correct the anatomy I see when I examine your face.
BEFORE & AFTER
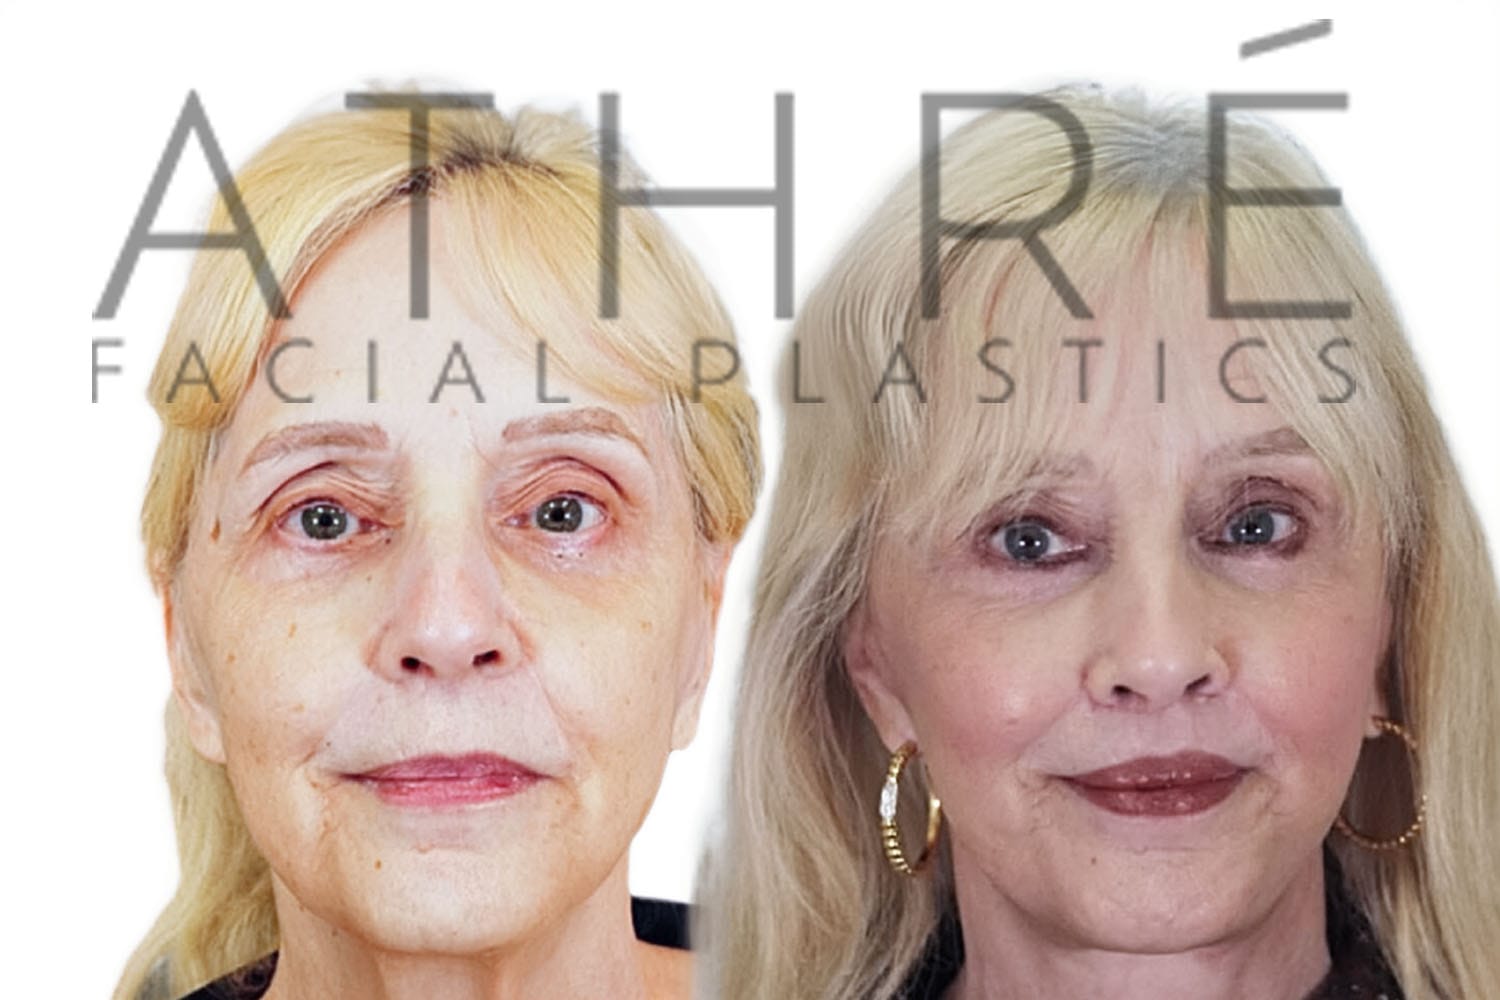
Facelift Results


FREQUENTLY ASKED
Mini Facelift vs. Endoscopic Deep Plane FAQs
The biggest distinction is where the aging is occurring. An RT Mini is primarily a lower-face, jawline and neck procedure, while an endoscopic vertical-vector deep plane lift is primarily addressing the midface and cheek.
Is an endoscopic deep plane facelift really scarless?
No. I don’t consider “scarless” an accurate description. The incisions are hidden within the hair-bearing scalp rather than placed in front of the ear, but incisions are still required.
Does an endoscopic facelift treat the neck?
Not directly. Endoscopic midface lifting is designed primarily to reposition descended cheek and midface tissues. If loose neck skin, platysmal banding or loss of neck definition is part of the problem, I need to evaluate whether a procedure that directly addresses the neck would be more appropriate. Published descriptions of endoscopic midface lifting similarly focus on repositioning the midface rather than comprehensive neck correction.
Does the RT Mini Facelift treat the midface?
It can provide some improvement depending on the anatomy and the extent of ligament release, but I primarily think of my RT Mini as a lower-face, jawline and neck procedure. A patient whose dominant problem is midface descent may be better suited to a procedure specifically designed to reposition that area.
Who is a good candidate for an endoscopic midface lift?
I am generally looking for midface or cheek descent, good skin quality and elasticity, and a patient who is genuinely happy with the jawline and neck. Patient selection is particularly important because endoscopic midface techniques reposition deeper tissues without relying on the skin excision used in more comprehensive facelift procedures.
How long does an endoscopic midface lift last?
There is evidence that improvement after endoscopic midface lifting can persist for years. One long-term study reported measurable improvement in patients followed for approximately 5 to 15 years after endoscopic midface surgery. That does not mean every endoscopic technique produces the same longevity, and it does not prove equivalence to an open deep plane facelift.
Is a deep plane facelift always better than a mini facelift?
No. I don’t choose a facelift simply because one technique sounds more advanced. Different operations address different anatomy, and the available evidence does not support treating one facelift technique as universally superior for every patient. A recent systematic review and meta-analysis of facelift techniques reinforces the importance of balancing outcomes, complications and patient-specific surgical planning.
How do I know which facelift I need?
I start with your anatomy rather than your age or the procedure name you walked in requesting. I look at the position of the cheek, the jawline, skin elasticity, neck laxity and the specific changes you want corrected. Facelift literature includes several effective surgical approaches, which is one reason procedure selection needs to be individualized rather than based on a single technique for every patient.



