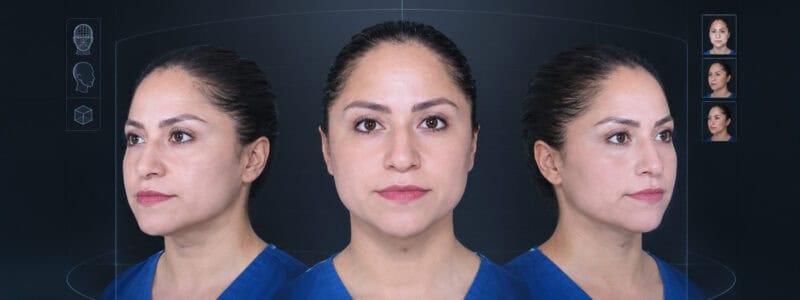
Most people associate rhinoplasty with younger patients who want to change the appearance of their nose. But I see another group of patients who are interested in nasal surgery for a very different reason. They are in their 40s, 50s, 60s or beyond, and their nose no longer looks quite the way it did when they were younger.
Sometimes these patients have always wanted to change something about their nose and have finally decided to pursue surgery. Other times, the concern is relatively new. Their nasal tip looks lower, their nose seems longer, or a hump that was always present has become more noticeable.
There is a reason for that. Just as our cheeks, jawline and neck change with age, the nose changes too.
We often hear that our nose and ears continue growing throughout life. The explanation is more complicated than that, but the observation is real. Nasal dimensions can increase over time, while changes in cartilage, ligaments, skin and underlying bone alter the shape and position of the nose.
That is also why rhinoplasty may be considered alongside a facelift. Rejuvenating the cheeks, jawline and neck does not automatically correct a nose that has become longer or developed a drooping tip.
There is no age at which someone automatically becomes too old for rhinoplasty. What matters is their health, nasal anatomy, goals and the operation required to achieve them.
UNDERSTANDING NASAL AGING
Does Your Nose Really Keep Growing as You Age?
Patients sometimes tell me they think their nose is getting bigger as they get older. In many cases, they are noticing a genuine change.
Our nose is not a completely fixed structure after adulthood. It continues to undergo changes in its dimensions, shape and supporting tissues.
But I want to distinguish those changes from the idea that nasal cartilage simply keeps growing larger at a constant rate throughout life.
The aging process involves several things happening together.
The Nasal Tip Begins to Descend
The nasal tip is supported by cartilage, ligaments and surrounding soft tissues. Over time, changes in the strength and elasticity of those structures can allow the tip to rotate downward.
When that happens, the nose may look longer, even if the patient has never had a particularly large nose.
Patients will sometimes show me photographs from 20 or 30 years earlier. Their nose may have had essentially the same underlying characteristics, but the tip was positioned differently.
That small change in position can have a significant effect on the profile.
The Supporting Structures Change
The bones of the face, nasal cartilage and connective tissues do not remain completely unchanged with age.
Alterations in those structures affect the relationship between the bridge, tip and base of the nose. The skin and soft-tissue envelope may also change in thickness and elasticity.
These changes are important during rhinoplasty because the operation must create a stable structure underneath the skin.
Simply removing cartilage from an aging nose without considering the support that remains can create problems with both appearance and breathing.
The Rest of the Face Changes Around the Nose
This is something I think patients often overlook.
As we age, the cheeks may lose volume, the midface changes and the tissues around the mouth begin to descend. Those changes alter the proportions of the face.
A nose that once looked balanced with fuller cheeks and a more youthful facial structure may begin to appear more prominent as the surrounding face changes.
In other words, the nose is aging, but so is everything around it.

THE AGING NOSE
Why the Nose Looks Different Over Time
Changes in nasal tip position, cartilage support and the surrounding facial structures can make the nose appear longer or more prominent. These changes can occur in both men and women and should be evaluated as part of the entire facial profile.
COMPREHENSIVE FACIAL REJUVENATION
Why Rhinoplasty Is Sometimes Combined With Facelift Surgery
This is an important part of facial rejuvenation that deserves more attention.
When patients come to me for a facelift, we spend time evaluating changes in the cheeks, jawline and neck. Those are areas where aging often creates visible sagging, jowls and loss of definition.
A deep plane facelift can reposition descended facial tissues, but it does not directly reshape the nose.
As a result, a patient may have a beautifully rejuvenated lower face while the nose still shows some of the structural changes associated with aging.
For example, the jawline may become better defined, and the cheeks may return to a more natural position. But if the nasal tip has descended significantly, that feature may remain noticeable against the refreshed facial contours.
In selected patients, combining rhinoplasty with a facelift allows me to address both concerns as part of the same overall surgical plan.
Creating Better Balance Across the Face
I think about facial proportions whenever I plan surgery.
The nose occupies the center of the face. It has a significant influence on how we perceive the eyes, cheeks, lips and chin.
If the nose has become longer or the tip has dropped, correcting that change may help restore balance with the other facial features.
That does not necessarily mean making the nose dramatically smaller.
For an older patient, I may be more interested in improving tip support, correcting a downward rotation or addressing an existing contour problem while preserving the character of the patient’s face.
There is a difference between creating a completely different nose and improving the proportions of the nose someone already has.
Particularly in facial rejuvenation, I often prefer an improvement that looks natural with the patient’s other features rather than a dramatic change that draws attention to the operation itself.
Can Rhinoplasty and a Facelift Be Performed During the Same Operation?
Yes, for appropriately selected patients.
The potential advantage is that we can coordinate changes in different areas of the face rather than treating each feature in isolation. Some patients also prefer the possibility of one surgical period and one overlapping recovery rather than two separate operations.
However, combining procedures is not automatically the right decision.
Rhinoplasty adds operative time and introduces its own swelling, healing requirements and potential complications. A complex nasal reconstruction combined with extensive facial rejuvenation may be better performed in stages.
I evaluate the patient’s medical history, the extent of each procedure, the anesthesia plan and the overall recovery before deciding whether a combination makes sense.
My goal is not to make every part of the face look younger independently. I want the nose, cheeks, jawline and neck to look balanced together.
That is the same philosophy behind my 4D Facelift™, which considers the different components of facial aging instead of assuming that lifting the tissues alone addresses every concern. Rhinoplasty can be considered as an additional procedure when the nasal anatomy also needs attention.
It is important to emphasize that not every facelift patient needs rhinoplasty. Many patients have a nose that remains proportionate to their face, and there is no reason to operate on it simply because they are undergoing facial rejuvenation.
RHINOPLASTY AFTER 40
What Should You Consider About Rhinoplasty in Your 40s?
In their 40s, many patients are not necessarily trying to reverse visible nasal aging. Some have simply reached a point in life when they are ready to address a concern they have had for years.
They may have disliked the appearance of a nasal hump since adolescence, noticed asymmetry after an old injury or struggled with breathing because of a structural nasal problem.
Other patients are beginning to notice subtle changes that were not present when they were younger.
The nasal tip may have started to rotate downward, or an existing hump may appear more prominent as facial proportions change.
When I evaluate someone in their 40s, I look at the nasal bridge, tip projection, cartilage support, skin characteristics and internal airway.
I also want to understand their goals. Are we correcting a long-standing feature? Are we addressing age-related changes? Or are both contributing to the concern?
In some patients, a dorsal preservation approach may be appropriate when the anatomy allows us to maintain more of the existing nasal architecture. Others require structural techniques to address tip position, asymmetry or breathing.
The operation needs to be selected for the nose, not simply for the patient’s decade of life.
I also would not assume that every patient in their 40s heals faster than every patient in their 60s. Medical history, smoking, previous surgery, skin characteristics and the complexity of the operation all influence recovery.
RHINOPLASTY AFTER 50
How Is Rhinoplasty Different in Your 50s?
In the 50s, I am often thinking more carefully about the relationship between the nose and the aging face.
The nasal tip may be lower than it was years earlier. The nose may appear longer, and changes in the cheeks and surrounding tissues can make its projection more noticeable.
At this stage, patients may also begin considering facial rejuvenation procedures.
Someone who is interested in a facelift may mention that their nose has changed, even though it was never a major concern earlier in life.
That is an opportunity to examine the nose as part of the overall facial assessment rather than assuming it is unrelated to facial aging.
For a patient who would benefit from both procedures, I may discuss a combined surgical plan. For someone whose concern is entirely nasal, rhinoplasty alone may be all that is necessary.
Why Structural Support Becomes Important
One of the mistakes I want to avoid in any rhinoplasty, but particularly in an aging nose, is reducing tissue without considering how the remaining structure will be supported.
The nasal tip and sidewalls need adequate support to maintain both their appearance and their function.
In some patients, grafts or other structural techniques may be necessary to maintain or improve that support.
I evaluate whether the existing cartilage is strong enough, how the tip is positioned and whether the patient has breathing concerns that need to be addressed at the same time.
The objective is not simply to create a smaller nose. It is to create a balanced nose that remains structurally sound.
RHINOPLASTY AFTER 60
Can You Have Rhinoplasty in Your 60s, 70s or Beyond?
Yes. I do not use a fixed upper age limit to decide whether someone can have rhinoplasty.
In fact, I have addressed this question directly in one of my videos. A healthy patient in their 70s or even 80s may still be an appropriate candidate for nasal surgery.
But that does not mean age is irrelevant.
As patients get older, I pay attention to medical conditions, medications, cardiovascular health, previous procedures and the way their tissues are likely to heal.
I also examine the strength of the nasal cartilage and the support of the nasal tip and sidewalls.
Age-related changes can contribute to nasal obstruction as well as changes in appearance.
Many patients in this group are not looking for a completely different nose. They want to restore support, correct an obvious change or improve breathing while maintaining their natural facial identity.
That can be a very reasonable objective.
But the operation must be appropriate for the patient’s anatomy and health, with realistic expectations about both the result and recovery.
INSIGHTS FROM DR. ATHRÉ
Is There an Age Limit for Rhinoplasty?
I explain that while younger patients must reach appropriate physical and emotional maturity before elective rhinoplasty, there is no fixed upper age limit. In older adults, the decision depends primarily on health, anatomy and surgical goals.
FORM AND FUNCTION
Can an Aging Nose Affect Your Breathing?
Absolutely. One of the reasons I think rhinoplasty should be approached as structural surgery is that the appearance of the nose and the way it functions are closely connected.
The nose is not simply an external shape. It is an airway supported by cartilage, bone and soft tissues. As the supporting structures change with age, certain patients develop increased nasal sidewall weakness or nasal valve collapse. These problems can contribute to breathing difficulty, particularly when airflow causes a weakened portion of the nasal sidewall to move inward.
Other patients have a deviated septum or changes related to an injury that occurred years earlier. In these cases, rhinoplasty planning may need to address function as well as appearance.
I want to understand whether an individual patient has breathing symptoms before recommending changes to the nasal structure.
A nose that looks beautiful but does not function properly is not the result I want to create.
INDIVIDUALIZED SURGICAL PLANNING
How Do I Plan Rhinoplasty for an Older Patient?
One of the things I have always emphasized is planning the operation before entering the operating room.
I evaluate photographs, facial proportions, nasal structure and the specific changes I believe are achievable. I want to understand the relationship between the nasal bridge, tip, chin and surrounding face.
For an older patient, I also consider whether the nasal changes are primarily structural or whether they are being accentuated by changes elsewhere in the face. This matters because making a nose smaller is not always the answer.
Sometimes the most important improvement involves supporting and repositioning the tip. In another patient, it may involve correcting an old dorsal deformity or improving the nasal airway.
And when the patient is planning a facelift, I evaluate how the proposed nasal changes will relate to the new facial contours.
In one of my videos, I show how I use photographs and measurements to develop a surgical blueprint. The purpose is to translate the patient’s goals and anatomical findings into a realistic operative plan.
I do not believe a computer simulation or an attractive photograph can replace that surgical reasoning.
Rhinoplasty should be designed around the nose that is actually in front of me, not an idealized nose from a photograph. The goal is to improve the patient’s own facial balance while preserving support and function.
BEHIND THE SURGICAL PLAN
How I Create a Rhinoplasty Surgical Blueprint
I demonstrate how photographs, measurements and detailed surgical drawings become a blueprint for rhinoplasty. The video shows why planning involves more than choosing the appearance of a nose on a screen.
HEALING AND RECOVERY
Does Rhinoplasty Recovery Take Longer When You Are Older?
Not necessarily. I have patients in their 60s who recover very well, and younger patients whose recovery requires more time. Chronological age is only one factor. I also consider overall health, skin characteristics, the quality of the nasal tissues and the extent of the procedure we are performing.
The complexity of surgery can have a significant influence on recovery. A patient undergoing primary rhinoplasty to address a relatively straightforward nasal concern may have a different experience from someone who needs extensive cartilage reconstruction or revision surgery. When I operate on a nose that has already undergone surgery, I may be working with scar tissue, altered anatomy and cartilage that has been weakened or removed. Those differences can affect swelling, healing and the amount of time it takes for the final result to become apparent.
For most patients, the first week involves the most visible swelling and bruising. As those early changes improve, patients gradually begin returning to normal social activities, although the timing varies. What I always emphasize is that looking presentable and being completely healed are two different things. The nasal tip, in particular, can retain swelling for several months, and the final refinements may take a year or longer to develop. Removing the nasal splint does not mean the nose has finished healing.
What If Rhinoplasty Is Combined With a Facelift?
When I combine rhinoplasty with a facelift, I plan the recovery around both procedures. There is an advantage to having overlapping recovery periods rather than undergoing two completely separate operations, but that does not mean recovery is identical to having a facelift alone. Rhinoplasty introduces additional swelling, nasal care requirements and restrictions that need to be considered alongside the healing of the face and neck.
I also think about what we can do before, during and after surgery to make recovery more manageable. Careful surgical technique, appropriate anesthesia, controlling bleeding and swelling, and consistent postoperative follow-up all contribute to that process. Depending on the individual patient, I may also incorporate some of the supportive treatments we use in our postoperative healing program. None of these measures eliminates the body’s natural healing process, but they allow us to approach recovery with the same attention to detail that we give the operation itself.
My goal is to give patients a realistic understanding of what recovery will involve. I would rather prepare someone for the possibility of prolonged swelling and have them recover more quickly than promise a specific timeline that their body may not follow.
MAKING THE DECISION
Am I a Good Candidate for Rhinoplasty After 40, 50 or 60?
When an older patient comes to see me about rhinoplasty, I start by asking what is bothering them about their nose and when they first noticed it. Sometimes it is a feature they have disliked since they were younger, such as a prominent dorsal hump or a wide nasal tip. Other times, they show me an old photograph and explain that their nose looks different now. The tip may have descended, the nose may appear longer, or changes elsewhere in the face have made the nose more prominent.
Those are different situations, and they may require very different surgical approaches. Someone who wants to correct a long-standing nasal deformity may need changes to the bridge, tip or underlying cartilage framework. Another patient may primarily need better structural support to correct age-related tip descent. If breathing has also become difficult, I need to determine whether the septum, nasal valves or other internal structures are contributing to the problem.
During the consultation, I examine the external nose, internal airway, skin thickness, cartilage strength and overall facial proportions. I also review the patient’s medical history and any previous nasal surgery. For older patients, these considerations are particularly important because I want to preserve or improve the support of the nose rather than simply remove tissue to make it smaller. A natural result depends on maintaining the relationship between nasal appearance and function.
I also ask whether the patient is considering other facial rejuvenation procedures. Someone planning a deep plane facelift may benefit from addressing age-related nasal changes during the same operation, particularly if the nasal tip has descended and no longer looks proportionate to the rest of the face. But combining procedures is not something I recommend automatically. If the nose already fits the patient’s facial proportions, there may be no reason to change it.
One of the things I find interesting about rhinoplasty in older adults is that many are not looking for a dramatic transformation. They often want to look like themselves, with a nose that feels more consistent with their facial features or the appearance they remember from earlier in life. A relatively subtle adjustment to tip position or nasal contour may be more appropriate than making the nose significantly smaller.
Ultimately, I do not believe someone should feel they missed their opportunity for rhinoplasty simply because they are no longer in their twenties. At the same time, I would never recommend surgery solely because the nose has changed with age. The decision should be based on a concern that matters to the patient, an achievable surgical goal and an acceptable level of risk.
The best age for rhinoplasty is not a particular birthday. It is the point when the patient has an appropriate reason for surgery, realistic expectations and the health to undergo the procedure safely.
You can explore examples of different nasal procedures in our rhinoplasty before and after gallery, or schedule a consultation to discuss what may be appropriate for your anatomy.
FREQUENTLY ASKED
Questions About Rhinoplasty in Older Adults
Age-related nasal changes, combining procedures, recovery and surgical candidacy are among the concerns patients raise when considering rhinoplasty later in life.
Does your nose continue to grow as you get older?
The nose can become measurably longer or change in shape over time, but this is not simply continuous cartilage growth. Age-related changes in skin, cartilage, connective tissue and facial bone affect the shape and position of the nose. A 2024 longitudinal study of nasal changes found increased nasal length and downward angulation of the tip over time.
Can rhinoplasty and a facelift be performed together?
Yes, in appropriately selected patients. A facelift primarily addresses descended facial tissues, while rhinoplasty can correct changes involving the nasal bridge, tip or structural support. A 2021 article on rhinoplasty as an adjunct to facial rejuvenation discusses the relationship between nasal aging and other facial changes. Combining surgery requires individual evaluation of health, operative time, anesthesia and recovery. Some patients benefit from staging the procedures instead.
Is 60 or 70 too old for rhinoplasty?
There is no fixed upper age limit. Candidacy depends on medical health, anatomy, surgical goals and the risks of the proposed procedure. A systematic review of rhinoplasty in patients over 55 describes the specific anatomical and functional issues that may require attention in older adults. Appropriate medical evaluation is more useful than an arbitrary age cutoff.
Why does the nasal tip droop with age?
The position of the nasal tip depends on cartilage, ligaments and other supporting tissues. Aging can alter these structures, contributing to downward tip rotation and an appearance of greater nasal length. A CT-based study of nasal aging documented changes in the tip, soft tissue and nasal bones. Depending on the anatomy, rhinoplasty may involve reinforcing support rather than simply removing tissue.
Can rhinoplasty make an older face look younger?
Rhinoplasty can improve certain nasal features associated with aging, such as a drooping tip or a nose that has become less proportionate to the face. However, it should not be presented as a guaranteed way to appear a particular number of years younger. A review of rhinoplasty in facial rejuvenation discusses how nasal changes can be addressed within the broader context of facial aging. The best result should remain balanced with the patient’s other features.
Can aging cause breathing problems that rhinoplasty may correct?
Changes in nasal cartilage and support can contribute to nasal valve problems in some older adults. Previous trauma or a deviated septum may also affect breathing. A clinical review of rhinoplasty in older patients describes nasal obstruction and structural collapse among the important considerations in this population. Surgery should address the specific cause of the obstruction rather than assuming every breathing complaint requires cosmetic rhinoplasty.
Will my nose keep changing after rhinoplasty?
Yes. Rhinoplasty changes the nasal structure but does not stop the normal aging process. Skin, connective tissues, cartilage and surrounding facial structures will continue to change over time. A longitudinal analysis of nasal shape changes documented changes in nasal dimensions within the same individuals over more than a decade. This is why preserving adequate support and planning for long-term facial balance matter.
Does rhinoplasty take longer to heal in your 50s or 60s?
Recovery varies according to overall health, the extent of surgery, skin characteristics and whether a patient has undergone previous nasal operations. Age alone does not establish a specific recovery timeline. The literature on rhinoplasty in older adults highlights the need to account for differences in anatomy and medical health during planning. Visible bruising and swelling may improve in the early weeks, while residual nasal swelling and final refinement can continue for a year or longer.