Most people think about rhinoplasty in terms of what they want to change: a hump on the bridge, a tip that looks too round, a nose that appears crooked or a profile that feels out of balance.
But when I plan a rhinoplasty, I am thinking just as much about what I need to preserve. The nose is a structure made of bone, cartilage, ligaments and soft tissue. It also has to move air. Changing one part can affect the way the other parts look and function.
There are four things about nose surgery that often surprise patients, even those who have spent years researching the procedure.
A good rhinoplasty is not simply about removing a bump or making a nose smaller. It is about improving its appearance while maintaining the structure that allows it to function.
01 / THE AIRWAY
Rhinoplasty Can Change How You Breathe, Not Just How You Look
Patients sometimes separate their concerns into two categories: a cosmetic nose job for appearance and a septoplasty for breathing. Anatomically, those problems are often connected.
The septum is the wall of cartilage and bone separating the nasal passages. It also provides important structural support. If the septum is crooked, it can contribute to nasal obstruction and may affect the outward shape of the nose. But the septum is not the only part of the airway I examine.
I also look at the internal and external nasal valves, the narrow regions through which air has to pass. If the sidewall of the nose is weak or collapses during breathing, simply straightening the septum may not solve the problem.
That is why I evaluate breathing before making aesthetic changes. Narrowing a nose without considering the airway can create a functional problem even when the external shape looks attractive.
I explain how these procedures overlap on my rhinoplasty versus septoplasty page.
02 / NASAL SUPPORT
Sometimes the Most Important Part of Rhinoplasty Is What I Do Not Remove
When someone wants a smaller nose, it is natural to imagine that surgery involves removing whatever seems too large. That can be part of the procedure, but removing tissue is not always the most effective way to create a stable result.
The cartilage of the septum and tip is the framework of the nose. If that framework becomes too weak, the nose can lose definition, change shape during healing or develop breathing problems.
For example, a rounded tip may need better cartilage positioning and support rather than simply having more cartilage cut away. A bridge with a hump may sometimes be treated by preserving its existing contour and repositioning the underlying framework instead of removing the hump from above.
Preservation and Structural Rhinoplasty Are Different Tools
With dorsal preservation rhinoplasty, I may be able to lower the nasal bridge while keeping more of the natural dorsal structure intact. In other cases, I need a structural approach involving cartilage reshaping or grafting.
When appropriate, I may use the Athré strut to help support tip position and definition. The choice depends on the strength and configuration of the patient’s existing cartilage, not on whether one technique has a more appealing name.
Previous nasal surgery changes this calculation. Scar tissue and missing or modified cartilage can make revision rhinoplasty more complex, and I may need cartilage from another source to rebuild support.
I am not trying to remove the greatest amount of tissue. I am trying to create the shape you want while leaving the nose with the support it needs for the years ahead.
03 / SURGICAL TECHNIQUE
Not Every Rhinoplasty Requires the Same Incisions or Bone Work
One of the questions I hear is, “Are you going to break my nose?” The answer depends on what needs to change.
If the nasal bones are already in a good position and the concern is primarily the tip, I may not need to reposition the bones. If the bridge needs to be narrowed, straightened or lowered, controlled bone work may be necessary.
When bone reshaping is appropriate, ultrasonic rhinoplasty gives me a powered instrument for precise work on the nasal bones. It does not mean every patient will avoid swelling or bruising, and it does not replace the need for careful planning.
Open and Closed Describe Access, Not the Quality of the Result
There is also confusion about open versus closed rhinoplasty. In a closed approach, I work through incisions inside the nostrils. With an open approach, I use those internal incisions plus a small incision across the columella, the strip of tissue between the nostrils, to provide additional exposure.
The closed approach avoids an external columellar incision. The open approach provides broader visualization, which can be useful for complicated anatomy or revision surgery. Neither one guarantees a better result simply because of the incision location.
I discuss the advantages and limitations on my open versus closed rhinoplasty page.
The question is not whether I can perform the surgery through the smallest incision. It is whether I have the access and technique needed to make the correct changes safely.
04 / THE HEALING PROCESS
You Can Feel Recovered Long Before Your Nose Has Finished Changing
Patients are often surprised by how different the early recovery period is from the longer process of seeing the nose settle into its final shape.
You may be back at work, exercising again after being cleared and living your normal life while residual swelling continues to resolve. This is particularly noticeable around the tip, where skin thickness, cartilage work and individual healing can influence how quickly definition becomes visible.
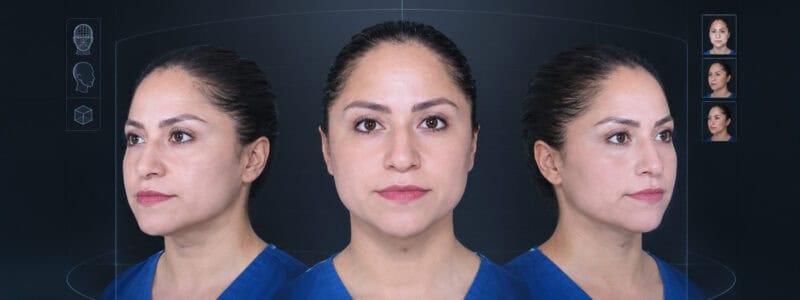
When I look at an early postoperative photograph, I know I am not looking at the final result. The same is true of a computer simulation. Imaging can help us talk about the plan, but it cannot predict exactly how the tissues will heal.
In my rhinoplasty consultation and 3D imaging process, I use imaging as a communication tool rather than a promise.
PATIENT FOLLOW-UP
What a Rhinoplasty Patient Says Two Years Later
At her two-year follow-up, Melissa describes how her nose continued to refine after she felt recovered from the initial surgery. Her experience helps show why early recovery and the final appearance of a rhinoplasty are not the same milestone.
What I Want You to Understand About Rhinoplasty Recovery
Melissa’s story is useful because she describes two separate experiences. She felt physically comfortable relatively early, but she continued noticing changes in the shape of her nose long afterward.
That was her experience, not a recovery schedule I can promise another patient. A rhinoplasty involving significant tip reconstruction, thicker skin, previous trauma or revision surgery may take longer to settle than a relatively limited primary procedure.
I would rather you understand that before surgery than judge the result too early. My goal is to create a nasal structure that looks balanced from different angles and functions well, then allow that structure time to heal.
For a closer look at the early postoperative period, see what to expect after a nose job.
REAL PATIENT RESULTS
Six Rhinoplasty Results, Six Different Starting Points
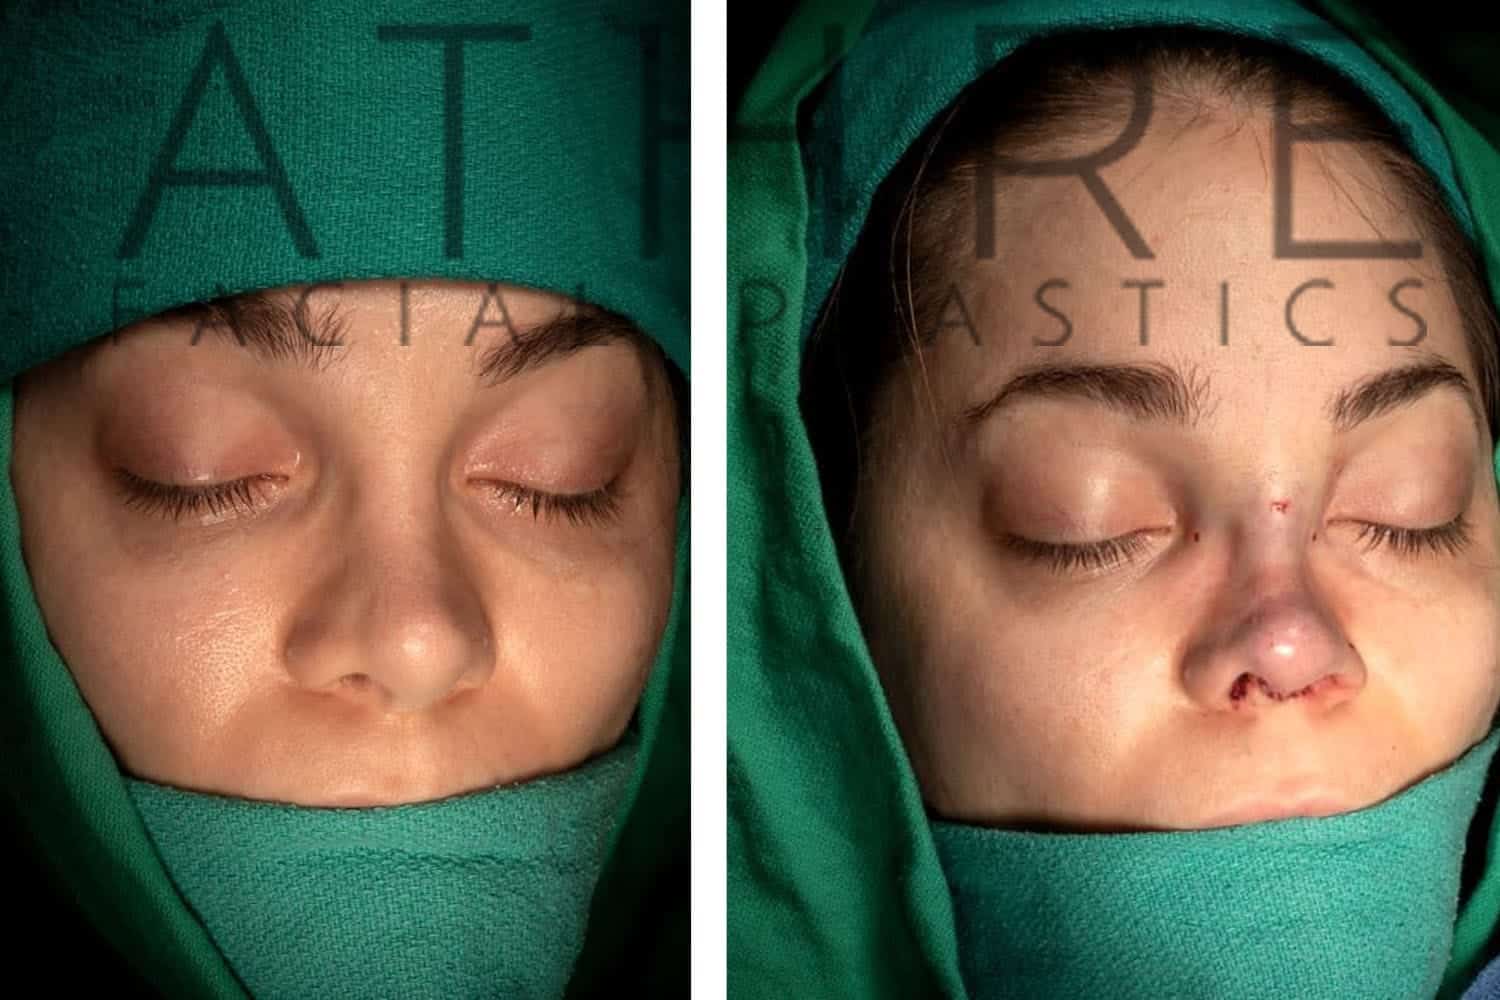
Look through these before and after photographs with the four points above in mind. One nose may need bridge refinement. Another may need better tip definition or a more involved structural correction. The goals are not identical, and neither are the anatomical decisions.
Photographs show changes in appearance, not the complete story of breathing, healing or the techniques used. Additional views are available in my rhinoplasty before and after gallery.
BEFORE & AFTER
Rhinoplasty Patient Results





What I Want to Know Before Recommending Nose Surgery
I start with the concern that brought you in. Is it the bridge? The tip? The frontal view? Your ability to breathe? Has the nose been injured or operated on before?
Then I look at the framework that is already there. I want to know what I can preserve, what needs to be changed and what may require additional support. I also want to understand how your nose relates to your chin, cheeks and the rest of your face.
I do not believe that every patient needs the same nose, the same incision or the same rhinoplasty technique.
The best surgical plan is not necessarily the one that removes the most tissue or uses the newest instrument. It is the one that addresses your goals while respecting your anatomy and nasal function.
FREQUENTLY ASKED
Frequently Asked Questions About Rhinoplasty Surgery
These are some of the questions patients ask when they learn how nasal structure, breathing, surgical technique and healing fit together.
Can rhinoplasty improve breathing as well as appearance?
Yes, when the breathing problem is related to anatomy that surgery can correct. The septum and nasal valves may need to be addressed along with the external shape of the nose. A meta-analysis of functional rhinoplasty for nasal obstruction found improvement in patient-reported breathing scores, although results varied between studies.
Is rhinoplasty the same surgery as septoplasty?
No. Rhinoplasty reshapes or reconstructs the nose, while septoplasty specifically addresses a deviated septum. The procedures can be combined when both the external anatomy and internal airway need treatment. A systematic review of septoplasty outcomes found substantial average improvements in patient-reported nasal obstruction after septoplasty with or without turbinate surgery.
Does every rhinoplasty require breaking the nasal bones?
No. Bone work depends on whether the bridge needs to be narrowed, straightened or repositioned. Some procedures focus primarily on the cartilage of the tip or septum. A review of preservation and structural rhinoplasty describes several ways surgeons can modify the nasal framework while preserving appropriate structures.
Is closed rhinoplasty better because it avoids an external scar?
Not automatically. Closed rhinoplasty avoids the external columellar incision, but open rhinoplasty may provide the exposure needed for more complicated corrections. A systematic review and meta-analysis comparing open and closed rhinoplasty found no consistent overall superiority of one approach in the outcomes studied.
Is dorsal preservation rhinoplasty better than traditional hump reduction?
It can be an excellent option in suitable anatomy, but it is not universally better. A systematic review comparing dorsal preservation and reduction techniques found tradeoffs between methods, including fewer dorsal irregularities but more residual or recurrent humps with preservation in the studies examined.
Why would I need cartilage grafts during a rhinoplasty?
Cartilage grafts may help support the tip, reinforce the nasal valves, straighten a structure or replace tissue that is missing. A review of structural and preservation rhinoplasty describes how grafting and tissue preservation can be selected or combined to meet different anatomical needs.
How long does swelling continue after rhinoplasty?
Much of the swelling improves early, but subtle changes can continue for months. In a three-dimensional study of postoperative nasal swelling, researchers measured continued reductions in edema through the first year after primary open rhinoplasty. Healing varies with the extent of surgery, skin thickness and individual tissue response.
Why is revision rhinoplasty more complicated than the first surgery?
A previously operated nose may contain scar tissue, altered anatomy and reduced cartilage support. A review of revision rhinoplasty techniques describes the additional planning and reconstruction sometimes needed, particularly when nasal valve support has been affected.